
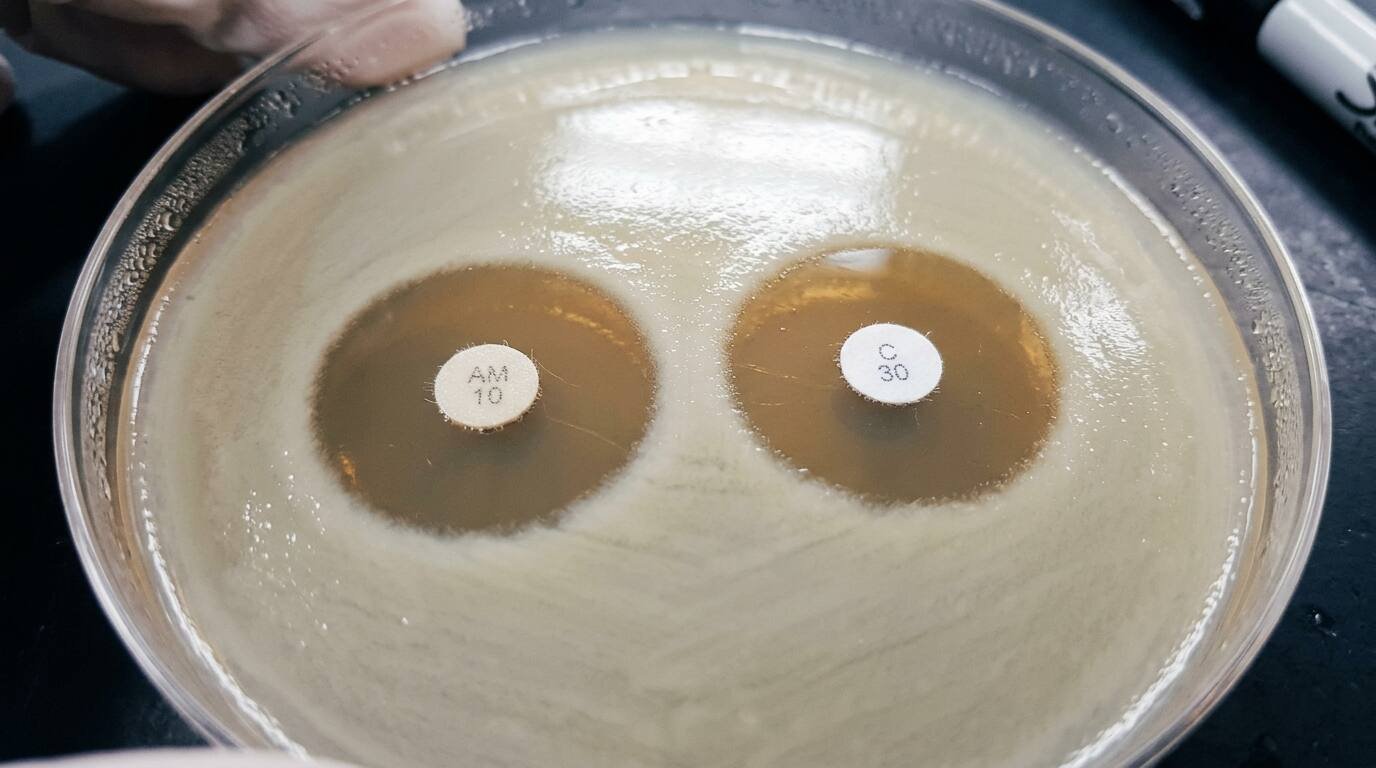
Antibiotic collateral sensitivity is the odd finding that a bacterium which evolves resistance to one drug can, as a side effect, become more vulnerable to another. If that trade-off were reliable, doctors could in principle use one antibiotic to push a pathogen into a weak spot and a second to hit it there, cycling back and forth so that resistance never gets a stable foothold. Twelve years after that idea was put forward as a clinical framework, nobody knows whether it works in patients.
Nothing here is treatment advice. It is a reading of the research literature.
The open question, stated precisely
Put plainly: can a planned sequence of antibiotics, chosen so that resistance to each drug sensitizes bacteria to the next, delay or prevent the emergence of multi-drug resistance in a real infection, compared with giving one drug until it fails and then switching?
Three things make the wording matter. “Delay” and “prevent” are different claims. The comparison has to be against what clinicians actually do, which is escalation after failure. And “a real infection” excludes the flask, where most of the evidence lives.
The idea of rotating drugs is not obscure. A biology study question hosted on Pearson’s Channels site asks students why letting doctors prescribe only a subset of antibiotics, and regularly rotating which ones are allowed, could limit the spread of resistance. Popular science coverage has run headlines as confident as “Rotating antibiotics stop superbugs” (The Naked Scientists). The textbook framing assumes the answer is yes. The research literature is much less sure.

What is established
- Collateral effects exist in both directions. The lowering of susceptibility to a second drug (collateral sensitivity) is real; so is the raising (cross-resistance), and in several experimental systems the second is more common.
- Drug order matters. In a modeling study using fifteen empirical E. coli fitness landscapes for beta-lactam antibiotics, none of the drug pairs commuted: giving A then B led to different end states than B then A (Nichol et al. 2015).
- Evolution under the first drug is not perfectly repeatable. Sixty replicate E. coli populations evolved under cefotaxime did not share one collateral profile across eight second-line drugs (Nichol et al. 2019).
- Ward-level rotation of drug classes has failed its one large randomized test. A cluster-randomized crossover trial in eight European intensive care units found no reduction in resistant Gram-negative carriage under cycling (van Duijn et al. 2018).
What is not established is the bridge between the first three facts and the fourth. Lab and model work speaks to a single lineage in a single host; the trial speaks to unit-wide prescribing across many patients and species. Neither tests the specific proposal: patient-level sequences tuned to the measured collateral profile of the infecting strain.
Hypothesis 1: collateral sensitivity cycles can trap bacteria
The strongest form of the optimistic case came from Lejla Imamovic and Morten Sommer at the Technical University of Denmark, who in 2013 proposed what they called collateral sensitivity cycling in Science Translational Medicine. As The Scientist summarized it, the authors argued that giving antibiotics in a deliberate order could both treat infections and slow resistance, and might also cut needless antibiotic use.
The logic is easy to state. If resistance to drug A comes with hypersensitivity to drug B and the reverse also holds, then every adaptive step the pathogen takes under one drug makes the next phase of treatment more lethal. A mutant that survives phase one is preferentially killed in phase two, and the double mutant has to arise from a reservoir that keeps getting purged.
Nichol and colleagues (2015) gave the idea a formal skeleton. They modeled evolution as a biased random walk on a fitness landscape, encoded as a Markov chain over sixteen genotypes, and asked which drug sequences could steer a population away from the most resistant peak of a final drug. With one steering drug, full prevention was possible for 3 of 15 target drugs; with pairs, 6; with triples, 7. So steering is possible in principle. That is the evidence for the hypothesis.
The same paper supplies the evidence against. Randomly chosen steering sequences often made things worse: single, paired and tripled steering drugs raised the likelihood of the most resistant genotype in roughly 57, 64 and 66 percent of cases. For two drugs, piperacillin plus tazobactam and ceftizoxime, random steering raised resistance in more than 80 percent of cases. The authors also showed that no general cycling strategy can return every starting genotype to where it began, which means a cycle only helps when you know the starting genotype. Their model assumed strong selection and weak mutation and ignored population size and drift; they said experimental validation was still needed.
Hypothesis 2: the trade-off is too unrepeatable to bank on
The sharpest challenge came from the same group. In the 2019 study, sixty replicate populations of E. coli carrying an SHV-1 beta-lactamase were evolved under cefotaxime and then tested against eight second-line antibiotics. Collateral sensitivity turned up, but rarely and never universally. In the preprint version of that work, piperacillin, ticarcillin-clavulanate and ampicillin-sulbactam each produced collateral sensitivity in some replicates and cross-resistance in others. Sequencing twelve replicates found five different SHV-1 variants. One replicate, carrying G238C, became more susceptible to three drugs; others carrying different changes did not.
The authors’ conclusion was that drug sequences designed from a single evolution experiment can overstate the benefit, and they put the requirement this way:
“the success of evolutionarily-informed therapies is predicated on a rigorous probabilistic understanding”
Nichol et al., Nature Communications, 2019
The steelman for this camp: a clinical infection is not one replicate. It is a population that may already contain several resistance routes, and the route that wins depends on chance. If collateral sensitivity holds in, say, half the lineages, a protocol built on it fails the other half, and fails them in the worst way, by selecting a strain that is cross-resistant to the drug you planned to use next. Against this view, one can argue that the problem is measurement, not biology. If the collateral profile of the actual infecting strain were read off at each step, the contingency would shrink. That is a testable engineering claim, not a refutation.
Hypothesis 3: cycling helps, but not because of collateral sensitivity
A third reading accepts that alternating drugs can slow resistance while denying that collateral sensitivity is the reason. Brepoels and colleagues at KU Leuven evolved Salmonella Typhimurium under cefotaxime and then exposed the resulting populations to second antibiotics at doses normalized to each population’s own minimum inhibitory concentration. That normalization removes the head start or handicap a collateral effect would give. Even so, the cefotaxime-adapted populations adapted more readily to ampicillin and tetracycline, and less readily to ciprofloxacin, chloramphenicol and kanamycin, than naive ones did (Brepoels et al. 2022).
Their title states the finding, and the abstract says that
“drug cycling can affect resistance evolution independently of collateral sensitivity”
Brepoels et al., Molecular Biology and Evolution, 2022
Collateral sensitivity was uncommon and weak in that system, while cross-resistance was common. The steepness of the first drug’s concentration gradient also changed the outcome: shallower gradients produced more competition among mutant lineages and lower fitness costs, which tracked with better adaptation to some second drugs. The implication is uncomfortable for both other camps. If the benefit of alternating drugs comes from history-dependent constraints on adaptation rather than a measurable trade-off, then measuring collateral profiles is the wrong guide, and so is abandoning cycling because those profiles are noisy.

The ward-scale trial, and why it does not close the question
The one large randomized test of rotation ran in eight European intensive care units between June 2011 and February 2014. Each unit ran a nine-month cycling period and a nine-month mixing period, separated by a one-month washout, with order randomized. Three antibiotic groups were rotated for empirical treatment of ICU-acquired Gram-negative infection: third- or fourth-generation cephalosporins, piperacillin-tazobactam and carbapenems. Under cycling the preferred group changed every six weeks; under mixing it changed with each consecutive course.
Resistant Gram-negative carriage ran about 23 percent during cycling (168 of 745 analyzed patients) and about 22 percent during mixing (184 of 853). The published interpretation begins:
“Antibiotic cycling does not reduce the prevalence of carriage of antibiotic-resistant, Gram-negative bacteria in patients admitted to the ICU.”
van Duijn et al., The Lancet Infectious Diseases, 2018
That is a real negative result and it should be taken seriously. But note what it tested. Six-week rotation of broad drug classes across a whole unit is a prescribing policy, not an evolutionary protocol: nothing matched a drug to the collateral profile of a given patient’s strain, and resistance was measured as carriage prevalence in a mixed, continually turning-over population with importation from outside. A policy that fails at that scale can still be right or wrong at the scale of one lineage in one patient. The honest version of the pro-cycling position concedes the mirror image: nobody has shown the patient-scale version does better.
A small simulation built for this article
To see which assumption does the heavy lifting, I wrote a stochastic birth-death model of a bacterial population inside one host and ran it in Python. It is a toy, not a model of any species or drug pair; its purpose is to compare schedules under assumptions I can state exactly.
The population carries five genotypes: wild type; two routes to drug-A resistance, one collaterally sensitive to drug B and one partially cross-resistant to it; a drug-B resistant genotype sensitive to A; and the double mutant. Growth is logistic with carrying capacity 109, offspring numbers are Poisson, mutation is binomial at 10-8 per division, and 400 replicate hosts run for 1,500 generations per schedule under a fixed seed. Two parameters are swept: the depth of collateral sensitivity, and p, the share of drug-A resistance mutations taking the cross-resistant route.
Schedules compared: drug A alone; drug A until the population rebounds past half of carrying capacity, then drug B for good (escalation after failure); and strict alternation every 2, 5, 10 or 25 generations.
import numpy as np
K, MU, GEN, REPS = 1e9, 1e-8, 1500, 400   # genotypes: WT, A-res(CS), A-res(cross), B-res(CS), AB

def fit(drug, d, x=1.2):
    if drug == 'A':
        return np.array([0.6, 1.9, 1.9, 0.6*(1-d), 1.8])
    return np.array([0.6, 0.6*(1-d), x, 1.9, 1.8])

def run(schedule, d, p, seed):
    rng = np.random.default_rng(seed)
    n = np.zeros((REPS, 5)); n[:, 0] = K
    t_multi = np.full(REPS, np.nan); t_fail = np.full(REPS, np.nan)
    cured = np.zeros(REPS, bool); failed_on_A = np.zeros(REPS, bool)
    FA, FB = fit('A', d), fit('B', d)
    for g in range(GEN):
        on_B = schedule(g, failed_on_A)
        w = np.where(on_B[:, None], FB, FA)
        lam = n * w / (1 + n.sum(1, keepdims=True) / K)
        new = rng.poisson(lam).astype(float)
        m_wa = rng.binomial(new[:, 0].astype(np.int64), MU)
        m_wb = rng.binomial(new[:, 0].astype(np.int64), MU)
        m_ax = rng.binomial(m_wa, p)                      # cross-resistant route
        m_ab = sum(rng.binomial(new[:, i].astype(np.int64), MU) for i in (1, 2, 3))
        new[:, 0] -= m_wa + m_wb; new[:, 1] += m_wa - m_ax; new[:, 2] += m_ax
        new[:, 3] += m_wb; new[:, 4] += m_ab
        n = np.maximum(new, 0); N = n.sum(1)
        cured |= (N == 0)
        fail = (N > K / 2) & np.isnan(t_fail) & (g > 5)
        t_fail[fail] = g; failed_on_A |= fail
        multi = (n[:, 4] > 0.5 * N) & (N > K / 10) & np.isnan(t_multi)
        t_multi[multi] = g
    return cured.mean(), np.mean(~np.isnan(t_multi)), np.nanmedian(t_multi)

mono = lambda g, f: np.zeros(REPS, bool)        # drug A forever
switch = lambda g, f: f.copy()                  # escalate after failure
def cyc(T): return lambda g, f: np.full(REPS, (g // T) % 2 == 1)
Selected results from that run (clearance means the simulated population hit zero; multi-resistance means the double mutant exceeded half of a population still above a tenth of carrying capacity):
| Schedule | CS depth | Cross-resistant route p | Cleared | Multi-resistant | Median generations to multi-resistance |
|---|---|---|---|---|---|
| Drug A alone | 0.5 | 0 | 1.5% | 0% | n/a (drug B never used) |
| Escalate after failure | 0.5 | 0 | 1.5% | 98.5% | 59 |
| Alternate every 5 | 0.5 | 0 | 100% | 0% | never |
| Alternate every 25 | 0.5 | 0 | 82.5% | 17.5% | 55 |
| Alternate every 5 | 0 | 0 | 40.3% | 59.8% | 228 |
| Alternate every 5 | 0.5 | 0.5 | 15.5% | 84.5% | 136 |
| Alternate every 5 | 0.9 | 0.5 | 18.3% | 81.8% | 136 |
| Escalate after failure | 0.9 | 0.5 | 1.5% | 98.5% | 70 |
Three patterns stand out, all of them properties of this model and not findings about bacteria.
- Deepening the trade-off buys almost nothing once a cross-resistant route exists. Going from no collateral sensitivity to a 90 percent growth penalty, with half of first-step mutations cross-resistant, moved clearance only from about 8 to 18 percent and left the median time to multi-resistance flat at roughly 135 generations.
- Closing the cross-resistant route is decisive. At the same trade-off depth, dropping p from 0.5 to 0 took clearance from 15.5 percent to 100 percent and eliminated multi-resistance in every replicate.
- Switch period matters more than the trade-off. Alternating every 25 generations instead of every 5, with the trade-off held at 0.5 and no cross-resistant route, cost 17.5 points of clearance, because each long block gives a single mutant time to reach a size from which the double mutant is likely.
What the simulation does not show: anything about real pharmacokinetics, immune clearance, spatial refuges, plasmid transfer, standing genetic variation at the start of treatment, or the many genotypes a real pathogen has available. It estimates no dosing interval. The row where plain alternation without any collateral sensitivity still delays multi-resistance nearly four-fold over escalation is a warning about interpretation, not a result about patients: in this model, single-drug resistance confers no protection against the other drug, and that reciprocal lack of cross-resistance is doing the work people usually attribute to sensitivity.

My reading, and what would settle it
Opinion, clearly labeled as such: the field has been arguing about the wrong parameter. Most experimental effort has gone into measuring how strong collateral sensitivity is between drug pairs, and most skepticism has gone into showing that those measurements are noisy across replicates. Both the modeling literature and the toy model above point elsewhere. It is the probability that the resistance routes available to the strain in front of you include one that is cross-resistant to your planned follow-up drug. A shallow but near-universal trade-off beats a deep but unreliable one.
If that reading is right, reporting conventions should change: a collateral sensitivity measurement without the fraction of replicates showing the opposite sign is close to useless for therapy design. Screen drug pairs for the absence of cross-resistant escape routes, not for mean sensitivity. And the right clinical unit is one patient’s lineage, sequenced during treatment, rather than a ward’s formulary.
Specific, falsifiable things that would move the question:
- Repeat the sixty-replicate design across several drug pairs and report, for each pair, the fraction of replicate lineages with collateral sensitivity, no change, and cross-resistance. Prediction: pairs will separate mainly by the cross-resistance fraction, and that fraction will predict the benefit of alternation in a follow-up competition experiment better than mean fold-change in minimum inhibitory concentration does.
- Run alternation against escalation in an animal infection model with whole-genome sequencing of the surviving population at each switch. Prediction: alternation wins only where no single mutation confers resistance to both drugs, and the size of the win tracks switch frequency more than trade-off depth.
- Test the Leuven result directly by normalizing second-drug doses to each evolved population’s own susceptibility in a second species and a second drug class. Prediction: history-dependent differences in adaptability persist, which would mean collateral profiles alone cannot predict cycling outcomes.
- A patient-level randomized trial in a setting with slow turnover and sequential cultures, such as chronic Pseudomonas infection, using sequence-guided drug order. This is the expensive one, and it only makes sense after the first three.
The gap between a plausible mechanism and a trial endpoint is not unique to this field; it also shapes what has actually been shown for AI-designed drugs. The population-genetics machinery behind the simulation above is the same machinery that answers older puzzles about how complex traits evolve by small steps, and the bacterial side of the story has its own arms race, visible in how bacteria switch on antiviral immunity against phage.
Common questions
Is collateral sensitivity the same thing as reversing resistance?
No. Collateral sensitivity means a strain that has become resistant to one drug is more susceptible than its ancestor to a second drug. The resistance to the first drug is still there. Reversal, in the sense of losing the resistance gene or mutation, is a separate process that depends on fitness costs and on the drug being withdrawn.
Didn’t the ICU trial prove rotation does not work?
It showed that rotating broad antibiotic classes every six weeks across a whole intensive care unit did not lower resistant Gram-negative carriage, in eight European units. That is strong evidence against rotation as a unit-level prescribing policy. It does not test drug sequences chosen for an individual patient’s strain, which is the version the evolutionary literature proposes.
Why does the order of two antibiotics change the outcome?
Because adaptation is path-dependent. The mutations that survive the first drug determine which further mutations are reachable and how costly they are. Nichol and colleagues found that none of fifteen empirical beta-lactam landscape pairs commuted, meaning A-then-B and B-then-A generally led to different end states.
Could cycling make resistance worse?
In the 2015 model, yes: randomly chosen steering sequences raised the chance of reaching the most resistant genotype in a majority of cases, and for two of the fifteen drugs in more than 80 percent. That is a model result, not a clinical one, but it is the reason the field treats untargeted sequencing as risky rather than merely unproven.
Is anyone using this in patients now?
Not as a validated protocol. The published work reviewed here is laboratory evolution, mathematical modeling and one negative ward-level trial. Any clinical use of a sequence-guided approach would be experimental and a matter for the treating team, not for general guidance.
References
- Nichol, D., Jeavons, P., Fletcher, A. G., Bonomo, R. A., Maini, P. K., Paul, J. L., Gatenby, R. A., Anderson, A. R. A., & Scott, J. G. (2015). Steering Evolution with Sequential Therapy to Prevent the Emergence of Bacterial Antibiotic Resistance. PLOS Computational Biology, 11(9), e1004493. doi:10.1371/journal.pcbi.1004493
- Nichol, D., Rutter, J., Bryant, C., Hujer, A. M., Lek, S., Adams, M. D., Jeavons, P., Anderson, A. R. A., Bonomo, R. A., & Scott, J. G. (2019). Antibiotic collateral sensitivity is contingent on the repeatability of evolution. Nature Communications, 10(1), 334. doi:10.1038/s41467-018-08098-6
- Nichol, D., et al. Preprint version of reference 2 (v4), bioRxiv 185892. biorxiv.org/content/10.1101/185892v4 (preprint; title page not retrieved)
- Brepoels, P., Appermans, K., Pérez-Romero, C. A., Lories, B., Marchal, K., & Steenackers, H. P. (2022). Antibiotic Cycling Affects Resistance Evolution Independently of Collateral Sensitivity. Molecular Biology and Evolution, 39(12), msac257. doi:10.1093/molbev/msac257
- van Duijn, P. J., et al. (2018). The effects of antibiotic cycling and mixing on antibiotic resistance in intensive care units: a cluster-randomised crossover trial. The Lancet Infectious Diseases. thelancet.com
- Imamovic, L., & Sommer, M. O. A. (2013). Collateral sensitivity cycling framework. Science Translational Medicine, 5(204), 204ra132. Article page as cited by reference 7: stm.sciencemag.org/content/5/204/204ra132 (title not verified from the publisher page)
- Vence, T. (2013). Giving Antibiotic Cycling Another Shot. The Scientist. the-scientist.com
- CIDRAP news staff (2018). Antibiotic cycling, mixing don’t affect resistance, study says. cidrap.umn.edu




[…] same exponential logic shows up wherever bacteria multiply, from antibiotic cycling strategies to phage therapy, and the leftovers question sits right next to the one x9m8 took on in US food […]